Connect with us

%

393,000 Long-Term Rental Homes Lost In Spain

Published

on

393,000-long-term-rental-homes-lost-in-spain

No long-terms rentals. Credit: Rocio X / Manuel Milan – Shutterstock

Spain has lost some 393,000 homes from its long-term rental listings in just seven years, according to new figures from property website Idealista.

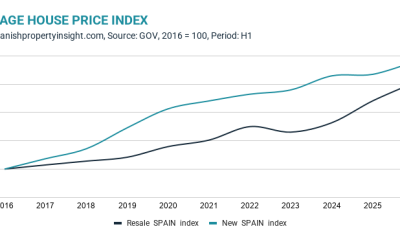
The number of homes advertised for permanent rental fell from 902,664 in 2018 to 510,091 in 2025, representing a 44 per cent reduction.

Idealista’s figures only count active long-term rental advertisements and exclude seasonal lets and rooms, so they do not mean that 393,000 homes have simply been left empty. However, the dramatic fall raises fresh questions about what is happening to properties that were previously available to long-term tenants.

Where have Spain’s long-term rental homes all gone?

The reduction has happened while rental prices have been moving in the opposite direction. Idealista’s latest figures show Spanish rents were 5.6 per cent higher in September 2026 than a year earlier, at an average of €15.10 per square metre. Malaga province was among Spain’s most expensive areas, at €18.80 per square metre, after a run of rises that has already pushed Malaga rents above Barcelona.

Some of the country’s biggest tourist and expat markets have seen particularly strong pressure. Andalucia lost 34,403 long-term rental listings between 2018 and 2025, falling from 136,003 to 101,600. The province of Malaga is now one of Spain’s most expensive rental markets, with the latest Idealista figures putting the average at €18.80 per square metre.

For foreign residents, the problem is particularly relevant because the supply of homes available to rent is already competing with demand from Spanish households, international workers, students and people moving to popular coastal areas. Some of that demand is already spilling inland, with foreign renters searching in Jaen and Badajoz, places that were almost unthinkable before for expat living.

Are landlords being pushed out of the market?

That question is becoming increasingly difficult to ignore as Spain introduces tighter rules for the rental sector. The latest Government housing measures include limits on rent increases, stronger protection for some tenants and restrictions affecting other parts of the rental market. Critics argue that increasing regulation can make some owners less willing to offer properties on the long-term market.

That does not necessarily mean every landlord is selling up or leaving a property empty, but some may have changed to seasonal rentals (AirBnB style), sell the property, use it themselves or simply decide that the potential legal and financial risks of becoming a landlord are not worthwhile.

That could include foreign owners who bought a second home in Spain and previously considered putting it on the long-term rental market when they were not using it themselves.

Landlords not the bad guys

Spain’s landlords are not simply big investment companies. More than 90 per cent of homes rented as habitual residences belong to private individuals who have just one rental property, according to a study by the Ministry of Consumer Affairs and the CSIC. These can be ordinary property owners who inherited a flat from a parent, for example, bought a second home when Spanish property prices were far lower, or acquired a property over many years and decided to rent it out. For such owners, becoming a landlord may be a relatively small part of their finances rather than a professional business. The question is whether increasingly complicated rental rules and concerns about recovering their property could persuade some of these owners to sell, leave their homes empty or choose another type of rental.

In the latest round of rental-law legislation, one of the measures that didn’t pass was that landlords would have had to pay back 12-month’s worth of rent to the tenant if they wanted to recover the property.

The Government disputes the idea that its policies are reducing the overall rental stock. Housing Minister Isabel Rodríguez has challenged the interpretation of the Idealista figures and says Spain has 380,000 more rented homes than in 2021.

Government figures also show that small private landlords still account for a substantial part of the rental market. A Ministry of Consumer Affairs and CSIC study found that private landlords with just one rented property account for around 39 per cent of rented homes, with the remainder held by landlords with multiple properties, companies, funds and public bodies.

Spain faces a serious rental supply dilemma

The competing figures underline the central problem facing Spain’s rental market. Protecting tenants can provide greater security for people already renting a home, but owners also need to believe that putting a property into the long-term rental market is worthwhile. Separate estimates already put Spain’s wider housing shortfall at around 740,000 homes.

With almost 393,000 fewer long-term rental advertisements than in 2018 and rents still rising, the question is no longer simply how Spain can protect tenants. It is also how the country can persuade enough property owners to keep offering homes to rent.

%

Daily Aspirin Guidance: Is Taking An Aspirin Every Day Still Safe?

Published

on

daily-aspirin-guidance:-is-taking-an-aspirin-every-day-still-safe?

Unwanted skin bruising and internal bleeding are key reasons medical guidance has moved away from routine daily aspirin for primary prevention. Credit: surprisestock/Shutterstock

For decades, taking a daily low-dose aspirin was widely regarded as simple, effective insurance against heart attacks and strokes. However, evolving clinical research, updated guidelines from NICE, and new 2026 medical consensus statements have shifted how doctors evaluate this common habit. While daily aspirin remains vital for patients with a history of cardiovascular events, taking it purely for primary prevention can carry a risk of internal bleeding that outweighs its protective benefits.

I thought I’d mention this because it is something people have been asking me about recently.

If you are getting older, have high blood pressure or cholesterol, or simply want to reduce your chances of having a heart attack, a daily low-dose aspirin has been regarded as a fairly harmless bit of insurance. I suspect quite a few people reading this have a packet of 75mg or 100mg aspirin somewhere in the bathroom cabinet.

But there is a problem with that apparently simple little tablet.

As I’m sure you know, aspirin can cause bleeding. And as our understanding of cardiovascular disease has improved, doctors have increasingly had to ask a rather uncomfortable question: Is the benefit of taking aspirin every day actually greater than the risk?

The answer depends very much on who you are.

Primary vs. Secondary Prevention: Who Actually Benefits from Aspirin?

The first thing to understand is the distinction between what doctors call primary and secondary prevention. If you have already had a heart attack, a stroke, or certain other forms of cardiovascular disease, aspirin may be prescribed to reduce the risk of another event. That is secondary prevention, and aspirin remains an important drug for many patients in that situation.

The controversy is about primary prevention – taking aspirin when you have never had a heart attack or stroke, but are taking it in the hope that it will stop one happening. And this is where the medical advice has changed.

In the UK, NICE (the organisation that looks at the use of medicines) no longer recommends routinely using aspirin for primary prevention. European guidance has also moved away from routine aspirin in people who do not already have cardiovascular disease because of the increased risk of major bleeding. But before those of us living in Spain start feeling smug about the British changing their minds, there is another twist.

Spain is moving in much the same direction. In 2025, the Spanish Society of Family and Community Medicine, reported on a review of 38 clinical guidelines and identified routine aspirin use for primary prevention as a practice of little or no preventive value because of the increased risk of bleeding.

So, this isn’t really a case of Britain saying one thing and Spain saying another. The science behind prescribing is changing in both countries. The problem is that medical practice doesn’t always change overnight.

How Aspirin Works in the Bloodstream and Causes Bleeding Risks

The reasoning behind aspirin was perfectly logical. Aspirin interferes with platelets – the tiny components of our blood that help form clots. A clot forming inside a coronary artery can block the blood supply to the heart and cause a heart attack. So, if aspirin makes the blood less likely to clot, surely it should reduce heart attacks?

Yes, it does.

The difficulty is that the same mechanism can also cause unwanted bleeding.

Aspirin doesn’t know whether the clot it is preventing is a dangerous one blocking an artery or the perfectly useful clot that would normally stop a small blood vessel in your stomach or intestine from bleeding. Consequently, aspirin can increase the risk of gastrointestinal bleeding and, more rarely but more seriously, bleeding inside the brain.

For somebody who has already had a heart attack, preventing another potentially fatal clot may be worth accepting that risk.

For somebody who has never had cardiovascular disease, the calculation is very different.

And that is the bit that has changed.

Ageing, Cardiovascular Prevention, and Updated 2026 Guidelines

There is another irony here. Many of us were originally told about daily aspirin as we got older because our risk of heart disease increases with age. But age also increases the risk of bleeding.

So, the very group that might theoretically gain more protection from aspirin is also the group in which the unwanted effects become more important.

Modern cardiovascular prevention has also changed the equation. We are much better at controlling blood pressure and cholesterol than we were several decades ago. Statins, better treatment of hypertension, smoking cessation and improved management of diabetes have all reduced cardiovascular risk.

That means the additional benefit obtained by giving aspirin to somebody who is otherwise receiving good preventive treatment may be relatively small.

A large body of evidence shows this rather neatly: aspirin can reduce some heart attacks and strokes in people without previous cardiovascular disease, but it also increases major bleeding, and it has not been shown to reduce overall mortality in this setting. A 2026 American College of Cardiology scientific statement describes the benefit as modest and stresses that aspirin should not be used routinely for primary prevention, particularly in older people.

In other words, we have become better at preventing heart attacks without necessarily needing aspirin to do it.

Should You Stop Taking Aspirin? Important Medical Considerations

This is where I would strongly urge caution.

If you are already taking aspirin because you have previously had a heart attack, stroke, coronary stent or another cardiovascular event, do not simply stop taking it because you have read this article. The reason you were prescribed it may be very important.

Equally, if you have been taking aspirin for years because someone once told you that it was a good idea “at your age”, it is reasonable to ask your doctor whether that advice still applies to you.

There is no universal answer.

Your doctor needs to consider your cardiovascular risk alongside your bleeding risk. Have you had cardiovascular disease before? Do you have high blood pressure, diabetes or high cholesterol? Do you smoke? Do you have a history of stomach ulcers or gastrointestinal bleeding? Are you taking other medicines that increase bleeding risk? These are much more important questions than simply asking whether you are over a particular age.

And please don’t confuse aspirin with anticoagulant medicines such as warfarin or the newer direct oral anticoagulants. They work differently and are prescribed for different reasons.

Deprescribing Trends and Modern Medical Practice in Spain

For those of us living here, there is an important practical point. Spain has not suddenly announced that everybody taking aspirin should stop.

Rather, Spanish medical organisations are increasingly saying that routine aspirin for primary prevention is not justified because the potential harm from bleeding can outweigh the cardiovascular benefit.

There is even Spanish research published in 2026 looking specifically at deprescribing aspirin – in other words, helping patients who were taking it for primary prevention to come off it when there was no longer a good reason for doing so.

That tells us something quite important. The question is no longer simply whether aspirin works. It clearly does.

The question is whether you are likely to gain enough from it to justify the risks.

Evolving Science: Asking Your Doctor the Right Questions

I think there is a wider lesson here that applies to much of modern medicine. Sometimes treatments become part of medical culture.

Doctors prescribe them. Patients expect them. We get used to taking them. And after twenty or thirty years it can be surprisingly difficult to question whether they are still necessary. But medical science doesn’t stand still. What was sensible advice in 1985 may not necessarily be sensible advice in 2026.

That doesn’t mean the doctors who prescribed aspirin all those years ago were wrong. They were working with the evidence available to them at the time.

Nor does it mean aspirin has become a dangerous or useless drug. Far from it. For some people it remains an extremely important medicine. What has changed is our understanding of who is most likely to benefit.

So, if you are taking a daily aspirin, don’t panic and don’t throw the packet in the bin. Instead, ask a much more useful question at your next appointment:

“Why am I taking this, and does the benefit still outweigh the risk for me?”

That, ultimately, is what good medicine should be about – not giving everybody the same answer, but making sure that the treatment is right for the individual.

And perhaps that little white tablet deserves rather more thought than we once gave it.

The information provided in this column is for educational and informational purposes only, and does not constitute medical advice. It is not a substitute for a professional medical consultation, diagnosis, or treatment. Always seek the advice of your own physician or other qualified health provider with any questions you may have regarding a medical condition.

Dr Marcus Stephan

Continue Reading

%

The Red Turtle Car – Part III

Published

on

the-red-turtle-car-–-part-iii

And there it is. The red turtle car. Credit: ozkan ulucam/Shutterstock

Last week, I left you going around in circles – quite literally – trying to understand Spanish roundabouts.

But just when I thought I had figured them out, another driving adventure was waiting: a toll booth, a missing credit card and one very slow red turtle car.

You might have thought that was the end of my driving adventures.

You would be wrong.

Take toll roads. You’re driving happily when suddenly you encounter one. Thirty kilometres an hour. Maybe forty if the driver is feeling adventurous. You know you are late. Finally, you overtake. You pass the turtle and watch as the red turtle-on-wheels car disappears into the distance.

You smile. “Finally! I can get there on time.”

Ah, yes. The toll booth – where the relaxing Costa del Sol drive suddenly becomes a frantic episode of:

Where’s the card?

You reach for your credit card. Where is it? You know you had it two minutes ago. Not there. Maybe the other pocket. Meanwhile, the machine raises an eyebrow and silently judges you as an impatient queue builds behind you.

“Please insert card.”

Yes, I know. I’m trying.

You find the card, insert it – and somehow drop it. Of course. Now you’re leaning halfway out of the window, trying to retrieve a tiny piece of plastic without rolling into the barrier. My career as a contortionist has officially begun.

You pick it up. Try again. Nothing. Now you’re sweating. You can almost hear them: “Come on, buddy. This isn’t your first toll booth.”

Finally, the machine accepts the card.

Victory!

The barrier rises and you pull away like someone who has just completed an Olympic event. You merge onto the motorway and look in the rear-view mirror.

And there it is. The red turtle car. The same red car you overtook ten minutes ago.

Somehow, he has paid his toll, passed through the booth and caught up with you while you were conducting a full financial transaction, gymnastics routine and minor emotional breakdown.

What exactly did you accomplish by overtaking him?

Nothing. Absolutely nothing.

Sound familiar? Isn’t that life sometimes? We rush, hurry and overtake, convinced we’re getting somewhere faster – only to discover a few minutes later, we’re alongside the person we were trying to overtake.

You spent petrol, raised your blood pressure, risked your dignity at the toll booth – and now you’re travelling together again.

And around and around we go – the great roundabout of life, where we race ahead, overtake, get stuck, take the wrong exit and somehow end up behind the same red turtle car.

Perhaps that’s the lesson.

Life isn’t a race. It’s a roundabout.

And frankly, I’m beginning to suspect the turtle knows the way better than I do.

And frankly, I’m loving it.

See you there!

Continue Reading

%

Cruise Entertainment Secrets: How It Works

Published

on

cruise-entertainment-secrets:-how-it-works

If you want something on stage every night, choose a line built that way. Credit: Solarisys / Shutterstock.com

Ask the Officer: Your cruise questions answered by a former senior ship’s officer

“Why did we never see the singers and dancers on our last cruise? We sailed fourteen nights and they were only on a few times. The year before, in the Caribbean, they seemed to be on almost every evening.”

You saw the same amount of theatre both times. The second cruise was just twice as long.

I had this conversation most weeks for fifteen years, usually somewhere between the atrium and the theatre doors, with a couple who’d been looking forward to those shows since booking. And I never had a satisfying answer for them, because the honest one is arithmetic, and arithmetic is a terrible thing to hand someone on their holiday.

Three shows. Almost always three.

A ship typically carries three production shows. Sometimes four, and the fourth is the runt of the litter, smaller in scale or built around a slimmer idea.

That is the whole inventory. It does not grow because your cruise is long. Three on a seven-night Caribbean, three on a fourteen-night Mediterranean, three on a twenty-one-night crossing. When a cast is hired, they learn those three and they maintain those three for the length of their contract, which might be six or eight months.

So on your Caribbean week, three productions plus four visiting acts cover nearly every evening and the ship feels like it is running a season. Put the same three across fourteen nights and the arithmetic becomes visible. Nothing was withdrawn. You just had more evenings in which to notice.

Why they can’t just carry more

Because a production show is one of the most expensive things a cruise line builds.

Choreography, direction, music licensing, technical design, lighting, sound, automation, costuming, and a rehearsal period that happens on land before anyone sets foot on the actual stage. One show lands somewhere between tens of thousands of dollars and the wrong side of half a million. The premium ones, with aerialists and water effects and automation that rebuilds the stage in front of you, get close to a million.

And they are worth watching. Full dance cast, live vocalists, lifts that rise and rotate, costumes that move like weather. Some ships have an ice rink. Some have a water theatre. All of it running on a vessel crossing open ocean, which is a trick no theatre in Madrid has to manage.

But nobody builds fourteen of them for one ship. If they did, either your fare would reflect it or the shows would, and it is usually the shows.

What fills the rest of the week

Everything else comes from what we call Guest Entertainers. Comedians, magicians, tribute acts, instrumentalists, the occasional variety troupe. They fly in, do a few nights, and move on to the next ship.

Quality is a lottery. Not because the acts are bad, but because chemistry with a particular audience is unpredictable. I have watched a comedian die on his feet on a Tuesday and destroy the room on the Thursday with the same material, the only difference being who had booked that cruise.

And then there are the cheap nights that guests consistently underestimate. Crew talent shows. Musician spotlights. The lounge band given a proper stage for once. They cost the cruise line almost nothing and they are, reliably, the evenings people tell me about years later. Partly low expectations. Mostly that watching the man who makes your bed sing an aria, badly, does something to a room that no amount of automation can buy.

I couldn’t outrun it

I did try.

I built programs specifically to make the cast visible offstage. Meet the cast sessions, deck appearances, lounge sets, pop-ups. Anything to put those faces in front of guests during the long middle stretch of a voyage when the theatre was dark.

It helped. It never fixed anything, because the problem was never effort. It was three and fourteen.

“We had shows almost every night in the Caribbean last year.” Yes. That was seven nights. This is fourteen. Same cast, same shows, twice the ocean.

When the sea takes one away

The other thing that empties a theatre is weather, and it happens fast.

Everything modern runs on automation. Lifts, tracks, winches, aerial rigs, all of it with a hard limit on wind and vessel motion. Past that limit, the systems are locked out. Sometimes a stripped-back version goes ahead, but you are not seeing the show anyone designed.

More often it moves to a calmer night. And if the rough stuff arrives on day eleven of a fourteen-night cruise, there is no calmer night left, so postponed quietly becomes cancelled.

This is true on the small luxury ships too, where the shows live in cabaret rooms with barely any automation at all. Dancers are athletes, but choreography in heels, with lifts and fast turns, stops being art and becomes an injury waiting to happen when the floor is moving.

And there is a layout reason the theatre suffers more than the rest of the ship. Main dining rooms need galley access, service corridors and provisioning routes, which puts them aft, and once the stern is spoken for, the theatre goes forward. So you end up watching a show in the part of the vessel that pitches hardest, which is fine in the Caribbean in February and much less fine crossing the Tasman. That alone will close a show.

Booking for what you actually want

Ask how many production shows the ship carries. Your agent can find out, and the line will tell you if you ask plainly.

If you want something on stage every night, choose a line built that way. You will get it, and you will also get lighter production values and the same faces so often that by Wednesday the novelty has gone. There is a casting reality underneath it too. Performing every night is a punishing contract, and the strongest singers and dancers tend to take the lighter rotations with better terms, which leaves a smaller pool for the lines that need somebody on stage six nights a week.

If three proper nights of shows is enough, take the long itinerary and plan the quiet evenings on purpose. That is what the speciality restaurant is for, and the slow drink afterwards, and the deck at ten o’clock when everyone else is inside watching a magician you were never going to enjoy.

Sara Romera is a former cruise ship officer and the author of Inside the Floating City and Love and Other Ports.

Have a cruise question? Write to contact@sararomera.com. Selected questions will be featured in upcoming columns.

Continue Reading

Trending

Copyright © 2017 Spanish Property & News